- The PCR test amplifies genetic matter from the virus in cycles; the fewer cycles required, the greater the amount of virus, or viral load, in the sample.
- The greater the viral load, the more likely the patient is to be contagious.
- The C.D.C.’s own calculations suggest that it is extremely difficult to detect any live virus in a sample above a threshold of 33 cycles.
- WHO Admits High-Cycle PCR Tests Produce COVID False Positives.
- Proof that COVID-19 Statistics are Being Padded With Influenza Cases.
- Researchers Uncover How the CDC Illegally Inflated COVID-19 Death Statistics
Your Coronavirus Test Is Positive. Maybe It Shouldn’t Be.
The usual diagnostic tests may simply be too sensitive and too slow to contain the spread of the virus
THE NEW YORK TIMES -- Some of the nation’s leading public health experts are raising a new concern in the endless debate over coronavirus testing in the United States: The standard tests are diagnosing huge numbers of people who may be carrying relatively insignificant amounts of the virus.
Most of these people are not likely to be contagious, and identifying them may contribute to bottlenecks that prevent those who are contagious from being found in time. But researchers say the solution is not to test less, or to skip testing people without symptoms, as recently suggested by the Centers for Disease Control and Prevention.
Instead, new data underscore the need for more widespread use of rapid tests, even if they are less sensitive.
“The decision not to test asymptomatic people is just really backward,” said Dr. Michael Mina, an epidemiologist at the Harvard T.H. Chan School of Public Health, referring to the C.D.C. recommendation.
“In fact, we should be ramping up testing of all different people,” he said, “but we have to do it through whole different mechanisms.”
In what may be a step in this direction, the Trump administration announced on Thursday that it would purchase 150 million rapid tests.
The most widely used diagnostic test for the new coronavirus, called a PCR test, provides a simple yes-no answer to the question of whether a patient is infected.
But similar PCR tests for other viruses do offer some sense of how contagious an infected patient may be: The results may include a rough estimate of the amount of virus in the patient’s body.
“We’ve been using one type of data for everything, and that is just plus or minus — that’s all,” Dr. Mina said. “We’re using that for clinical diagnostics, for public health, for policy decision-making.”
But yes-no isn’t good enough, he added. It’s the amount of virus that should dictate the infected patient’s next steps. “It’s really irresponsible, I think, to forgo the recognition that this is a quantitative issue,” Dr. Mina said.
The PCR test amplifies genetic matter from the virus in cycles; the fewer cycles required, the greater the amount of virus, or viral load, in the sample. The greater the viral load, the more likely the patient is to be contagious.
This number of amplification cycles needed to find the virus, called the cycle threshold, is never included in the results sent to doctors and coronavirus patients, although it could tell them how infectious the patients are.
In three sets of testing data that include cycle thresholds, compiled by officials in Massachusetts, New York and Nevada, up to 90 percent of people testing positive carried barely any virus, a review by The Times found.
On Thursday, the United States recorded 45,604 new coronavirus cases, according to a database maintained by The Times. If the rates of contagiousness in Massachusetts and New York were to apply nationwide, then perhaps only 4,500 of those people may actually need to isolate and submit to contact tracing.
One solution would be to adjust the cycle threshold used now to decide that a patient is infected. Most tests set the limit at 40, a few at 37. This means that you are positive for the coronavirus if the test process required up to 40 cycles, or 37, to detect the virus.
Tests with thresholds so high may detect not just live virus but also genetic fragments, leftovers from infection that pose no particular risk — akin to finding a hair in a room long after a person has left, Dr. Mina said.
Any test with a cycle threshold above 35 is too sensitive, agreed Juliet Morrison, a virologist at the University of California, Riverside. “I’m shocked that people would think that 40 could represent a positive,” she said.
A more reasonable cutoff would be 30 to 35, she added. Dr. Mina said he would set the figure at 30, or even less. Those changes would mean the amount of genetic material in a patient’s sample would have to be 100-fold to 1,000-fold that of the current standard for the test to return a positive result — at least, one worth acting on.
The Food and Drug Administration said in an emailed statement that it does not specify the cycle threshold ranges used to determine who is positive, and that “commercial manufacturers and laboratories set their own.”
The Centers for Disease Control and Prevention said it is examining the use of cycle threshold measures “for policy decisions.” The agency said it would need to collaborate with the F.D.A. and with device manufacturers to ensure the measures “can be used properly and with assurance that we know what they mean.”
The C.D.C.’s own calculations suggest that it is extremely difficult to detect any live virus in a sample above a threshold of 33 cycles. Officials at some state labs said the C.D.C. had not asked them to note threshold values or to share them with contact-tracing organizations.
For example, North Carolina’s state lab uses the Thermo Fisher coronavirus test, which automatically classifies results based on a cutoff of 37 cycles. A spokeswoman for the lab said testers did not have access to the precise numbers.
This amounts to an enormous missed opportunity to learn more about the disease, some experts said.
“It’s just kind of mind-blowing to me that people are not recording the C.T. values from all these tests — that they’re just returning a positive or a negative,” said Angela Rasmussen, a virologist at Columbia University in New York.
“It would be useful information to know if somebody’s positive, whether they have a high viral load or a low viral load,” she added.
Officials at the Wadsworth Center, New York’s state lab, have access to C.T. values from tests they have processed, and analyzed their numbers at The Times’s request. In July, the lab identified 794 positive tests, based on a threshold of 40 cycles.
With a cutoff of 35, about half of those tests would no longer qualify as positive. About 70 percent would no longer be judged positive if the cycles were limited to 30.
In Massachusetts, from 85 to 90 percent of people who tested positive in July with a cycle threshold of 40 would have been deemed negative if the threshold were 30 cycles, Dr. Mina said. “I would say that none of those people should be contact-traced, not one,” he said.
Other experts informed of these numbers were stunned.
“I’m really shocked that it could be that high — the proportion of people with high C.T. value results,” said Dr. Ashish Jha, director of the Harvard Global Health Institute. “Boy, does it really change the way we need to be thinking about testing.”
Dr. Jha said he had thought of the PCR test as a problem because it cannot scale to the volume, frequency or speed of tests needed. “But what I am realizing is that a really substantial part of the problem is that we’re not even testing the people who we need to be testing,” he said.
The number of people with positive results who aren’t infectious is particularly concerning, said Scott Becker, executive director of the Association of Public Health Laboratories. “That worries me a lot, just because it’s so high,” he said, adding that the organization intended to meet with Dr. Mina to discuss the issue.
The F.D.A. noted that people may have a low viral load when they are newly infected. A test with less sensitivity would miss these infections.
But that problem is easily solved, Dr. Mina said: “Test them again, six hours later or 15 hours later or whatever,” he said. A rapid test would find these patients quickly, even if it were less sensitive, because their viral loads would quickly rise.
PCR tests still have a role, he and other experts said. For example, their sensitivity is an asset when identifying newly infected people to enroll in clinical trials of drugs.
But with 20 percent or more of people testing positive for the virus in some parts of the country, Dr. Mina and other researchers are questioning the use of PCR tests as a frontline diagnostic tool.
People infected with the virus are most infectious from a day or two before symptoms appear till about five days after. But at the current testing rates, “you’re not going to be doing it frequently enough to have any chance of really capturing somebody in that window,” Dr. Mina added.
Highly sensitive PCR tests seemed like the best option for tracking the coronavirus at the start of the pandemic. But for the outbreaks raging now, he said, what’s needed are coronavirus tests that are fast, cheap and abundant enough to frequently test everyone who needs it — even if the tests are less sensitive.
“It might not catch every last one of the transmitting people, but it sure will catch the most transmissible people, including the superspreaders,” Dr. Mina said. “That alone would drive epidemics practically to zero.”
https://cnas.ucr.edu/media/2020/08/29/your-coronavirus-test-positive-maybe-it-shouldnt-be
Read the original article here:
VIEW ARTICLE
___
WHO Admits High-Cycle PCR Tests Produce COVID False Positives
Written by Tyler Durden

Were the ‘conspiracy theorists’ just proven right about the “fake rescue plan” for COVID? Did the ‘science-deniers’ just get confirmation that it was political after all?
The short answer to both of these questions regarding the COVID-19 ‘casedemic’ and the fallacy of asymptomatic PCR testing is YES and YES!
We have detailed the controversy surrounding America’s COVID “casedemic” and the misleading results of the PCR test and its amplification procedure in great detail over the past few months.
As a reminder, “cycle thresholds” (Ct) are the level at which widely used polymerase chain reaction (PCR) test can detect a sample of the COVID-19 virus. The higher the number of cycles, the lower the amount of viral load in the sample; the lower the cycles, the more prevalent the virus was in the original sample.

Numerous epidemiological experts have argued that cycle thresholds are an important metric by which patients, the public, and policymakers can make more informed decisions about how infectious and/or sick an individual with a positive COVID-19 test might be. However, as JustTheNews reports, health departments across the country are failing to collect that data.
In fact, as far back as October, we brought the world’s attention to the COVID-19 “casedemic” and the disturbing reality of high-cycle threshold PCR tests being worse than useless as indicators of COVID-19 “sickness”. PJMedia’s Stacey Lennox said at the time:
Biden will issue national standards, like the plexiglass barriers in restaurants he spoke about during the debate, and pressure governors to implement mask mandates using the federal government’s financial leverage.
Some hack at the CDC or FDA will issue new guidance lowering the Ct the labs use, and cases will magically start to fall.
In reality, the change will only eliminate false positives, but most Americans won’t know that.
Good old Uncle Joe will be the hero, even though it is Deep-State actors in the health bureaucracies who won’t solve a problem with testing they have been aware of for months. TDS is a heck of a drug.
And now, as Lennox explains in detail below, we have been proved 100% correct as less than one hour after President Biden’s inauguration, the WHO proved us right.
In August of last year, The New York Times published an article stating that as many as 90% of COVID-19 tests in three states were not indicative of active illness. In other words, they were picking up viral debris incapable of causing infection or being transmitted because the cycle threshold (Ct) of the PCR testing amplified the sample too many times.
Labs in the United States were using a Ct of 37-40. Epidemiologists interviewed at the time said a Ct of around 30 was probably more appropriate. This means the CDC’s COVID-19 test standards for the PCR test would pick up an excessive number of false positives. The Times report noted the CDC’s own data suggested the PCR did not detect live virus over a Ct of 33. The reporter also noted that clinicians were not receiving the Ct value as part of the test results.
Yet a PCR test instruction document from the CDC that had been revised five times as of July 13, 2020, specified testing and interpretation of the test using a Ct of 40. On September 28, 2020, a study published in the journal Clinical Infectious Diseases from Jaafar et al. had asserted, based on patient labs and clinical data involving nearly 4,000 patients, that a Ct of 30 was appropriate for making public policy. An update to the CDC instructions for PCR testing from December 1, 2020, still uses a Ct of 40.
Shortly before the New York Times article was published, the CDC revised its COVID-19 test recommendations, saying that only syptomatic patients should be tested. The media went insane, and Dr. Fauci went all over television saying he was not part of the decision to change the testing standards:
“I am concerned about the interpretation of these recommendations and worried it will give people the incorrect assumption that asymptomatic spread is not of great concern. In fact it is.”
So, of course, the Mendacious Midget™ had spoken, and the guidelines went back to testing everyone, all the time, with an oversensitive test.

The idea that asymptomatic spread was a concern as of August was just one of many lies Dr. Fauci told. At the beginning of the pandemic in late January, he said:
The one thing historically that people need to realize is that even if there is some asymptomatic transmission, in all the history of respiratory borne viruses of any type, asymptomatic transmission has never been the driver of outbreaks. The driver of outbreaks is always a symptomatic person. Even if there is a rare asymptomatic person that might transmit, an epidemic is not driven by asymptomatic carriers.
There is not a single study or meta-analysis that differs from Fauci’s original assessment.
Today, within an hour of Joe Biden being inaugurated and signing an executive order mandating masks on all federal property, the WHO sent out a notice to lab professionals using the PCR test. It said:
WHO guidance Diagnostic testing for SARS-CoV-2 states that careful interpretation of weak positive results is needed (1).
The cycle threshold (Ct) needed to detect virus is inversely proportional to the patient’s viral load.
Where test results do not correspond with the clinical presentation, a new specimen should be taken and retested using the same or different NAT technology.
literally one hour after Biden takes the oath, the WHO admits that PCR testing at high amplification rates alters the predictive value of the tests and results in a huge number of false positives pic.twitter.com/iDtXmappRw
— Andy Swan (@AndySwan) January 20, 2021
This translates to “in the absence of symptoms, a high Ct value means you are highly unlikely to become ill or get anyone else sick in the absence of very recent exposure to an infected person.”
Dr. Fauci knew this in July when he said that tests with a Ct above 35 were likely picking up viral debris or dead virus.
Even at a Ct of 35, the incidence of virus samples that could replicate is very low, according to Jaafar et al.
The only state I know that requires reporting the Ct with every test is Florida, which started this policy in December.
The WHO went on, stating:
Most PCR assays are indicated as an aid for diagnosis, therefore, health care providers must consider any result in combination with timing of sampling, specimen type, assay specifics, clinical observations, patient history, confirmed status of any contacts, and epidemiological information.
In short, a positive PCR test in the absence of symptoms means nothing at a Ct of higher than 30, according to the experts interviewed by the New York Times and according to Jaafar et al. Yet positive tests is the number CNN loves flashing on the screen.
If the percentage found by the Times in August holds, there have been approximately 2.43 million actual cases to date, not 24.3 million.
There is also no way to calculate the deaths from COVID-19 rather than deaths with some dead viral debris in the nostrils.
What I have referred to as the “casedemic” since September will be magically solved just in time for Joe Biden to look like a hero. For doing absolutely nothing.
Do not tell me there is not a politicized deep state in our health agencies. Do not ever tell me I need to listen to Dr. Anthony Fauci again. And every business owner who has been ruined because of lockdowns due to a high number of “cases” should be livid. Any parent whose child has lost a year of school should be furious.
None of this was for your health. It was to get rid of Orange Man Bad.
now they will drop the cycle rates and you can watch the curve go negative… like magic… because the new magic man isn’t the bad man and the masks he ordered worked!!!!!
— Andy Swan (@AndySwan) January 20, 2021
As an aside, this also clearly explains the disappearance of the “flu” during this season as the plethora of high Ct PCR Tests supposedly pointing to a surge in COVID are nothing of the sort.
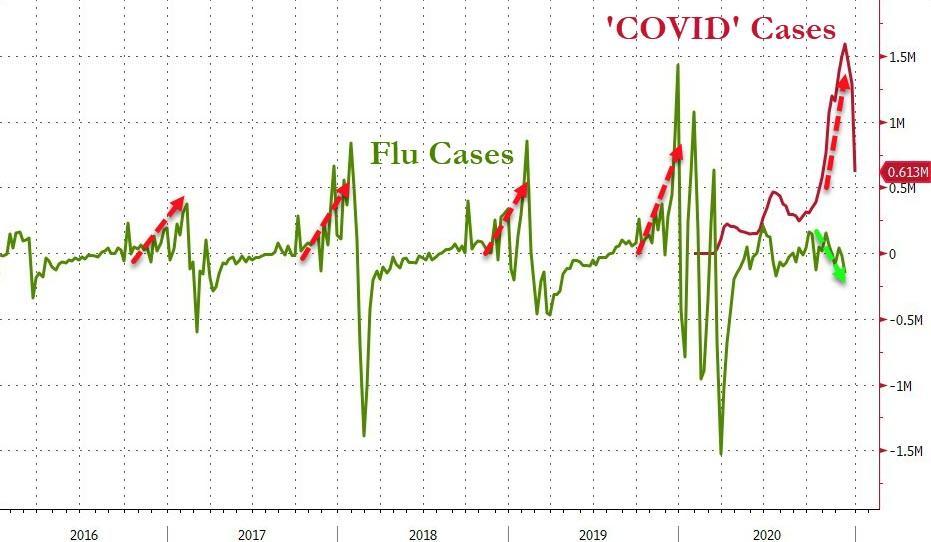
As Stephen Lendman noted previously, claiming “lockdowns stopped flu in its tracks, (outbreaks) plummet(ting) by 98% in the United States” ignored that what’s called COVID is merely seasonal influenza combined with false positives (extremely high Ct) from PCR-Tests.
And for that reason, the great 2020 disappearing flu passes largely under the mass media’s radar. Media proliferated mass deception and the power of repetition get most people to believe and having successfully “killed the flu”, they will now do the same with COVID… and, if allowed by our betters, we will all return to the new normal they desire.
https://principia-scientific.com/doctors-nurses-giving-covid-19-vaccine-will-be-tried-as-war-criminals/?utm_source=feedburner&utm_medium=email&utm_campaign=Feed%3A+psintl+%28Principia+Scientific+Intl+-+Latest+News%29
Read more at www.zerohedge.com
___
Proof that COVID-19 Statistics are Being Padded With Influenza Cases
Below are a series of three short videos of an interview by software engineer and statistician John Cullen of Dr. (and State Senator) Scott Jensen. While Cullen calls Dr. Jensen a hero, and he is, Cullen is every bit worthy of that accolade. I cannot do justice with the treasure of information coming from these two patriots, and so I will set forth below my simple explanation of the World Health Organization (WHO) influenza data discussed by Cullen. The charts reveal that the COVID-19 statistics are being padded by falsely reporting influenza cases as COVID-19 cases.
To suggest that influenza cases are being misrepresented as COVID-19 cases is simply not allowed to be mentioned in the mainstream media. Peter Andrews, writing for Russia Today, reveals that there has been a 98% plummet in flu infections. He then reveals it is impolite within the scientific community to suggest that doctors are misclassifying influenza cases as COVID-19 cases. Andrews explains that “it only seems like the flu has disappeared because doctors and scientists have been wrongly classing other respiratory diseases as Covid. Please note that the boffins are already treating this suggestion as something akin to flat-Earth theory.”
Andrews reveals that “Australia essentially ‘skipped’ their flu season this year, with not a single case reported since July (their peak). In fact, flu has more or less vanished throughout the Southern Hemisphere.” Andrews was writing on October 29, 2020. The Southern Hemisphere had emerged from what should have been their fall and winter flu season. But they had none. And the Northern Hemisphere since followed suit with a collapse in reported flu cases. Jo MacFarlane reporting for The Daily Mail concluded from the WHO data that “flu, it seems, has all but vanished.”
MacFarlane published his article on October 24, 2020, which was the beginning of what is supposed to be the fall and winter flu season in the Northern Hemisphere. MacFarlane could already see from the data that the expected seasonal flu epidemic was not making its appearance. The reported flu cases in the UK were down approximately 90%. He saw the disappearance of the flu revealed by “the figures provide a startling insight into what has become a creeping trend across the world.”
Of course, MacFarlane states the obvious. “There are those who claim flu cases haven’t vanished at all, but are instead being recorded as Covid-19.” But after making that common-sense statement, MacFarlane quickly dismisses the thought. So, what is the explanation he announces for the disappearance of the flu in the midst of the alleged COVID-19 pandemic? It is the theory of … wait for it … “viral interference.”
MacFarlane explains that “[w]hen an individual is infected with one virus, they are less likely to be infected by another during that time due to something called ‘viral interference’.” MacFarlane quotes Dr. Elisabetta Groppelli who claims that “[v]iruses are parasites. Once they enter a cell, they don’t want other viruses to compete with. So the virus already in the body will effectively kick the other parasite out.” It sounds good, but it is not true. Indeed, when one’s immune system is focused on fighting off one particular pathogen, the body’s immune resources are focused on that pathogen. With all of the body’s immune resources focused on that one pathogen, the person does not have the reserves to fight an unrelated pathogen and is thus is more susceptible to an unrelated pathogen.
That is why the flu vaccine only works for the particular strain of the flu virus that is in the vaccine and no others. Often, persons who receive the flu vaccine end up getting the flu, but it is a different strain of the flu for which they have no protection. Under the theory of ‘viral interference’ the patient getting a flu shot should be protected from all strains of flu and not just the strain in the vaccine.
The phenomenon of a vaccinated person being more susceptible to an unrelate pathogen is known as pathogenic priming. Vaccines cause pathogenic priming, which injures a person’s immune system such that the person is 4.4 times more likely to become ill from some other pathogen. For example, at least six major studies have shown that a person who gets the flu shot has had their immune system pathogenically primed to be more likely to become infected from coronavirus.
The charts below reveal a complete collapse in worldwide cases of influenza after COVID-19 made its appearance in the spring of 2020. Notice the complete disappearance of the flu during the 2020-2021 fall and winter seasonal flu period. That disappearance of flu correlates directly with the reported second-wave of COVID-19 cases and suggests that flu cases are being misreported as COVID-19 second-wave cases.


Researchers Uncover How the CDC Illegally Inflated COVID-19 Death Statistics
__
eof